Physical Address
304 North Cardinal St.
Dorchester Center, MA 02124
Physical Address
304 North Cardinal St.
Dorchester Center, MA 02124

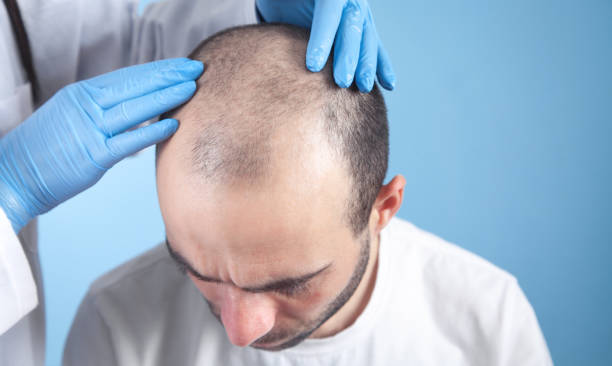
A receding hairline changes the proportions of the upper face as the frontal and temple areas gradually lose density. Hair Transplant in Al Ain can restore suitable areas by relocating healthy follicles from the donor region and positioning them to follow the patient’s natural growth pattern.
Hairline restoration is one of the most detail-sensitive areas of hair transplantation. The objective is not simply to lower the forehead but to create a transition that remains believable from close range and at different angles.
Male pattern hair loss commonly affects the temples and frontal hairline first.
The recession may begin subtly, with the corners becoming thinner before the central hairline changes significantly.
The temples require careful planning because they sit at the junction between the forehead and the sides of the face.
If grafts are inserted too densely or at an incorrect angle, the restored area may look disconnected from the surrounding hair.
As recession progresses, the frontal hairline can move backward while the existing hair becomes finer.
The surgeon needs to distinguish between follicles that have completely disappeared and those that are still producing miniaturized hair.
A transplanted hairline remains visible every time the patient looks in a mirror.
For that reason, design has to account for age, facial proportions, hair calibre and expected future loss.
Natural hairlines contain small variations.
A slightly irregular leading edge can create a softer transition between the forehead and transplanted hair. A rigid, perfectly straight border can look artificial.
Hair follicles do not emerge vertically from the scalp.
The angle becomes particularly important around the frontal region because the hair needs to transition naturally into existing growth.
The surgeon therefore considers direction and angulation when preparing recipient sites.
Not every follicular unit is equally suitable for the leading edge.
Single-hair units can provide a delicate transition at the front, while larger follicular units may be positioned behind the first line where greater density is appropriate.
The donor area must contain enough healthy follicles.
Hair calibre and follicular-unit composition can influence the visual density achieved from a given number of grafts.
A receding hairline may be visually important, but it should not consume the entire donor reserve.
Future hair loss needs to be considered before determining how aggressively the frontal region should be restored.
FUE allows individual follicular units to be harvested from the donor area.
The surgeon can then select and position appropriate grafts for different parts of the hairline.
The extraction pattern matters because concentrated harvesting can create visible thinning in the donor area.
Younger patients sometimes want a dramatically lower hairline.
That approach can use a significant amount of donor hair and may leave fewer resources available if recession continues later.
The hairline should be designed with the patient’s expected long-term pattern in mind.
A conservative design can leave room for future changes while still improving the current facial frame.
A hairline appropriate for a younger face may not look equally natural decades later.
The surgeon therefore considers the patient’s facial structure and age rather than using a universal measurement.
“If my temples are receding, I should lower the entire hairline.”
Not always. Some patients primarily need temple restoration rather than a substantial change to the central frontal hairline.
“More grafts automatically mean a better hairline.”
Density is only one part of the result. Placement direction, graft selection, spacing and long-term donor preservation also matter.
“A transplant stops future male pattern hair loss.”
It does not necessarily stop ongoing loss in untreated native follicles. Long-term hair-loss management may therefore remain important after transplantation.
The early recovery period focuses on protecting newly placed grafts.
Patients may experience temporary redness, mild swelling or crusting around the recipient area. The exact recovery experience varies according to the individual and the extent of treatment.
Patients living in Dubai should also consider the UAE climate when planning recovery. Strong sunlight, outdoor activities and heavy exercise may need to be limited temporarily according to postoperative instructions.
Transplanted hair does not normally produce an instant finished hairline.
Some of the visible transplanted hair can shed after the procedure while the follicle remains within the scalp.
New growth develops progressively, and the appearance continues to mature over subsequent months.
For patients researching receding hairline restoration in Al Ain, the consultation should focus on more than the number of grafts.
The key questions are how much donor hair is available, which follicles are appropriate for the frontal edge, how far the hairline should be restored and how the design will accommodate future changes.
A carefully planned hairline should complement the patient’s face rather than draw attention to the transplant itself.
Hair restoration is a long-term decision.
Preserving donor density, protecting existing native hair and avoiding an excessively aggressive hairline can help maintain options for the future.
For patients considering an individualized restoration plan, Tajmeels Clinic provides consultation-led hair-transplant planning based on the patient’s hair-loss pattern, donor characteristics and aesthetic goals.